 Vietnamnet.vn

 Podcast


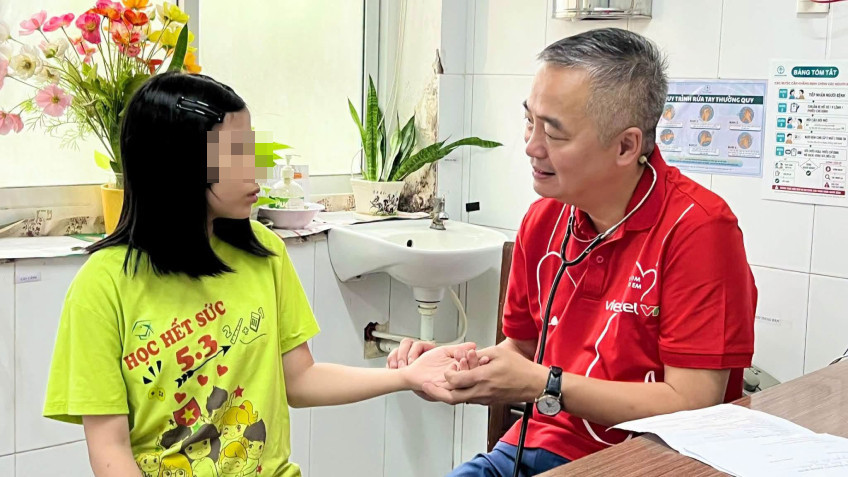
Match Day is an annual event held by Hanoi Medical University on September 9 to announce results of the residency doctor exam and allow newly graduating doctors to choose their residency specialties.
There have been calls to change the way residency specialties are selected, including a proposal to return to the system of registering for a specialty before taking the residency entrance exam.
VietNamNet presents below the views of Associate Professor Nguyen Lan Hieu, director of the Hanoi University of Medicine Hospital, on the issue of choosing residency specialties.
I still vividly remember my decision to pursue cardiology more than 30 years ago.
At the time, we had to choose a specialty before taking the residency entrance exam and compete with others who shared the same interests for a very limited number of residency positions.
There were 450 students in our class, but only 30 residency positions, or less than 10 percent. To be eligible for the exam, students had to have scored above 7 in the final grade for their chosen specialty and have graduated with at least a fairly good academic standing.
Yet the competition was not particularly intense. There was a specialty with two positions available, and there were only two applicants. So, before choosing a specialty, most of us would find out who we would be competing against. If we faced a particularly strong rival, many would withdraw, choose another specialty or even decide not to take the exam at all.
The way residency recruitment is organized today is quite different from our time. The changes have certainly brought many improvements, but I believe there are still some aspects that are not entirely reasonable and need serious consideration.
First, we are asking students to choose a career before they have had a chance to understand it.
During medical school, students may spend only two months on cardiology, two months in respiratory medicine and so on. With such limited exposure, how can they already know whether they truly love and are suited to a specialty they may spend the rest of their lives practicing?
In the US, doctors choose a subspecialty only after completing three years of general residency training. They have three years to gain experience, discover what they like, become tired of certain fields, explore different areas and draw inspiration from different mentors.
We, by contrast, are asking students to make their choices when they still have very little experience to draw on.
Second, this system unintentionally creates a ‘hot vs. cold’ specialty bias.
In every Matching season, the same questions start circulating: “What score will it take to get into cardiology this year?” “Is surgery still a hot specialty?”
We are turning a deeply humane decision - choosing where one will build a career and serve patients - into a race for scores.
I have seen many students who were very well suited to pathology, allergy and other specialties that do not rank among the highest-scoring choices but are facing a shortage of highly qualified doctors. Yet because students achieve high exam scores, they think, “Why would I pass up” specialties considered hot, such as plastic and aesthetic surgery or obstetrics?
Eventually, some of them are unhappy with the choices they made.
The fault does not lie with the students. It lies in the way we have organized the system.
There are no “cold” specialties in medicine. There are only doctors who are cold toward their patients.
A skilled surgeon may successfully perform a difficult operation, but that does not mean their contribution is more valuable than that of a respiratory specialist who detects lung cancer at an early stage.
Third, we should train good internists before training specialists.
We need to train good internal medicine doctors before training specialists in cardiology, hematology, emergency and critical care, and other fields.
Currently, surgery, obstetrics and pediatrics are following this approach: Students receive common training at the beginning and only choose the subspecialty they intend to pursue long-term when they are working on their graduation theses.
Instead of Matching too early to immediately divide students into specialties, we should have them enter residency through broad groups such as internal medicine, surgery, obstetrics and pediatrics, as we did in the past. The first two years should be a genuinely common training period.
Phuong Thuy

