 Vietnamnet.vn

 Podcast


Heart condition discovered after football injury
Clayton David Andrew, a 43-year-old British national living in Vietnam, regularly participates in sports, including football, swimming and running.
After suffering a rib injury while playing football, Andrew visited a hospital, where doctors discovered that he had severe mitral valve regurgitation.
After exploring treatment options, he sought a comprehensive cardiac assessment at the University Medical Center Ho Chi Minh City.
Examinations revealed that Andrew had severe primary mitral regurgitation caused by Barlow's disease, a degenerative condition affecting the mitral valve.
Notably, although he had not experienced obvious symptoms, his heart chambers were already showing signs of enlargement.
His left ventricular end-systolic diameter had exceeded 40mm, while changes in the heart's pumping function were beginning to emerge.
These findings indicated that the condition was no longer simply an abnormality detected through echocardiography but had begun affecting the heart's structure.
Professor Nguyen Hoang Dinh, Deputy Director of the hospital, explained that when the mitral valve fails to close properly, some blood flows backward from the left ventricle into the left atrium with each heartbeat.
If the condition persists, the heart must work harder, potentially causing progressive enlargement of its chambers and deterioration in its pumping function.
Therefore, decisions about surgical intervention cannot be based solely on whether patients feel healthy or experience fatigue.
Doctors must comprehensively assess the severity of valve regurgitation, heart chamber dimensions, left ventricular function and the feasibility of repairing the valve.
Complex heart valve repaired through a 4cm incision
According to Dr. Pham Tran Viet Chuong from the Department of Cardiovascular Surgery, Barlow's disease is a complex degenerative condition affecting the mitral valve.
The valve tissue is typically thickened and excessive, while multiple segments of both valve leaflets may bulge or prolapse.
The supporting chordae tendineae may become elongated or rupture, and the valve annulus can become enlarged.
Because abnormalities may occur simultaneously in several areas, surgeons must carefully evaluate each component to determine the most appropriate repair technique.
The objective is to restore proper valve closure while preserving as much of the patient's natural valve tissue as possible.
In Andrew's case, a large section of the P2 segment of the posterior mitral valve leaflet had prolapsed, accompanied by ruptured chordae tendineae.
Rather than replacing the damaged valve with an artificial prosthesis, the surgical team chose to repair the existing mitral valve.
Preserving the natural valve, along with its chordae tendineae and papillary muscles, is important for maintaining the geometry and function of the left ventricle.
Depending on the type of prosthetic valve and the patient's individual circumstances, repair can also help avoid certain disadvantages associated with artificial heart valves.
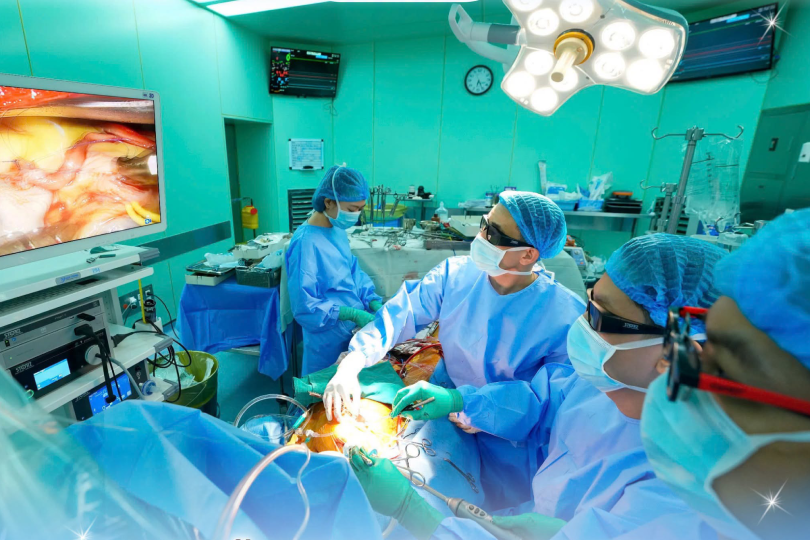
A particularly notable aspect of the procedure was that surgeons treated the complex valve abnormalities using minimally invasive endoscopic surgery.
Instead of opening the sternum, as required in conventional open-heart surgery, the team accessed the heart through an incision measuring approximately 4cm on the right side of the chest, along with a smaller incision for a camera.
Working within the confined surgical space required exceptional precision.
The surgeons identified the prolapsed valve segment, reconstructed the damaged chordae tendineae to the appropriate length and implanted an annuloplasty ring to restore the mitral valve's structure and function.
After the procedure, intraoperative transesophageal echocardiography confirmed that both ventricles were contracting effectively and that significant mitral regurgitation was no longer present.
Andrew recovered well following surgery, with stable hemodynamic parameters, and was successfully taken off mechanical ventilation just five hours after the operation.
A follow-up examination one week later continued to show positive recovery signs.
Dr. Chuong emphasized that severe mitral regurgitation can progress silently over many years.
Patients diagnosed with the condition should undergo regular follow-up examinations to monitor changes in cardiac structure and function, allowing doctors to determine the most appropriate time for intervention.
He warned that patients should not wait until they experience shortness of breath, fatigue or symptoms of heart failure before seeking medical attention, as their cardiac function may already have been significantly affected by that stage.
Phuong Thuy

